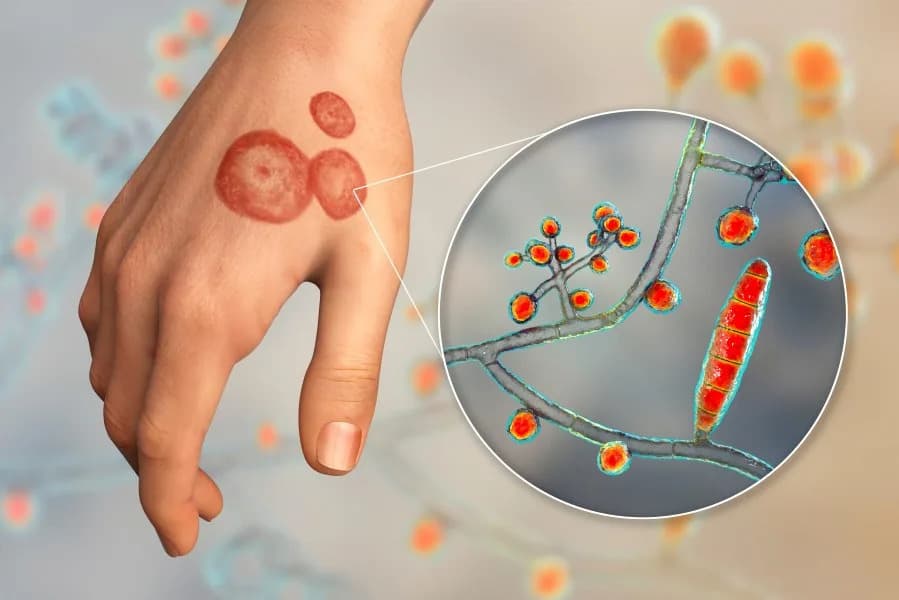
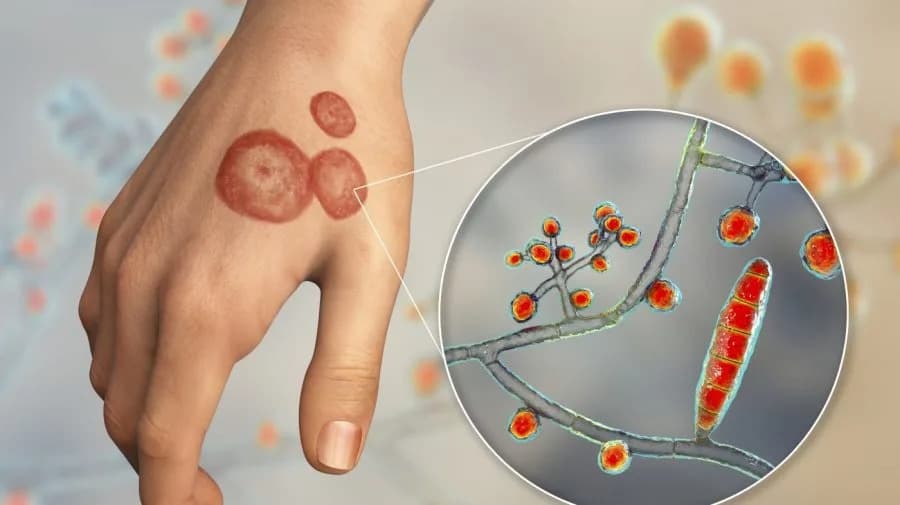
The CDC reports 3,437 clinical cases of drug-resistant Candida auris across 27 U.S. states as of the week ending July 25, 2026, with California reporting 873 cases. C. auris can survive on surfaces, colonize people without symptoms, and spreads easily in healthcare settings. Most at risk are patients with severe conditions or invasive devices; invasive infections are linked to high mortality and frequent antifungal resistance. The CDC classifies C. auris as an urgent antimicrobial-resistance threat, and strict infection-control plus ongoing research are critical.
Drug-Resistant Candida auris Detected in 27 U.S. States — 3,437 Clinical Cases Reported
Woman in hospital
Provisional Centers for Disease Control and Prevention (CDC) data show 3,437 clinical cases of the drug-resistant yeast Candida auris in 27 U.S. states as of the week ending July 25, 2026. California accounts for the largest share with 873 reported clinical cases.
Key Data
Other states with high counts include Texas (433), Tennessee (283), Ohio (279), Georgia (193), Louisiana (179), Illinois (171), Arizona (171), Michigan (146), Virginia (132) and Pennsylvania (121). All remaining states report fewer than 100 clinical cases each.
Thousands of cases of a potentially deadly, drug-resistant fungus have been reported across 27 states so far this year, according to provisional CDC data.
What Is Candida auris?
Candida auris is a species of yeast that can cause severe infections, particularly in healthcare settings such as hospitals and nursing homes. It can survive on surfaces for extended periods and is easily transmitted between patients via contaminated surfaces and shared equipment (for example, bedrails, doorknobs and medical devices).
Colonization vs. Infection
The CDC defines a clinical case as detection of C. auris in a specimen collected during routine medical care. Some positive specimens reflect colonization — where a person carries the organism without symptoms — rather than an active infection. Colonized individuals can still spread the organism to others.

As of the week ending July 25, a total of 3,437 clinical cases of Candida auris (C. auris) had been documented in the U.S. so far in 2026.
Who Is Most At Risk?
People most vulnerable to invasive C. auris infections include patients with serious underlying medical conditions and those who use invasive devices such as breathing tubes, feeding tubes, intravenous lines or urinary catheters. Patients who are hospitalized frequently or for extended periods are also at higher risk. Healthy people without these risk factors are unlikely to become colonized or develop disease.
Symptoms, Outcomes and Treatment
Symptoms of invasive infection are nonspecific (fever, chills, body aches) and can be mistaken for other illnesses. Reported mortality rates for invasive C. auris range from about 30% to 72%, although many patients who die are already critically ill, which complicates determining the fungus’s direct contribution to death.

Those most at risk of infection include patients with severe underlying medical conditions. In particular, those who use breathing tubes, feeding tubes, IVs or catheters are more vulnerable, as are those who are hospitalized frequently or for long periods of time.
C. auris often shows resistance to common antifungal medications. More than 90% of U.S. samples are resistant to fluconazole, a widely used antifungal. Echinocandins are currently the primary treatment option, but some strains exhibit resistance to all three major antifungal classes, making infections difficult to treat. The CDC classifies C. auris as an "urgent antimicrobial-resistance threat."
"It is resistant to multiple antifungal drugs, and it tends to spread in hospital settings, including on equipment being used on immunocompromised and semi-immunocompromised patients," said Dr. Marc Siegel, senior medical analyst and clinical professor of medicine at NYU Langone.
Prevention and Research
Strict infection control measures — including routine screening in high-risk settings, thorough sterilization and disinfection of equipment and surfaces, and careful hand hygiene — are essential to limit spread. Major research efforts are underway to develop new antifungal treatments and diagnostics.
Reporting for this story included contribution from Angelica Stabile of Fox News Digital.
Help us improve.