The author uses a viewing of I Am Legend to warn against declaring miracle cures. New MHRA figures link weight‑loss injections such as Wegovy and Mounjaro to 98 UK deaths (some analyses suggest up to 216) and about 150,000 reported side effects, with many serious events tied to tirzepatide. While millions report significant benefits, the piece highlights real concerns — from loss of appetite and hair loss to weight regain after stopping and unequal access — and urges calm, evidence‑based risk‑benefit assessments.
‘Miracle’ Weight‑Loss Drugs Weren’t The Answer — MHRA Data Raise Alarms

Caroline Savage died after upping her dose of Mounjaro and suffering faecal peritonitis - Susannah Savage / SWNS
I spent a pleasant evening this week watching the dystopian 2007 thriller I Am Legend, which opens with a scientist unveiling a measles‑derived genetic cure for cancer. Predictably, that supposed salvation wipes out most of humanity and turns others into violent, nocturnal mutants. The film’s silly premise nonetheless underlines a durable truth: there are no miracle cures. Even common medicines can harm a small number of people — for example, some react badly to aspirin, and my husband is among the few who are severely allergic to penicillin.
That is why I instinctively distrust drugs hailed as panaceas without a clear discussion of risks. History shows that initial enthusiasm is often followed by rare but serious harms. The UK’s AstraZeneca Covid vaccine, once widely celebrated, was later linked to very rare cases of dangerous blood clots, including the death of BBC presenter Lisa Shaw. Such episodes underline the importance of reading the fine print and weighing benefits calmly before starting a new treatment.
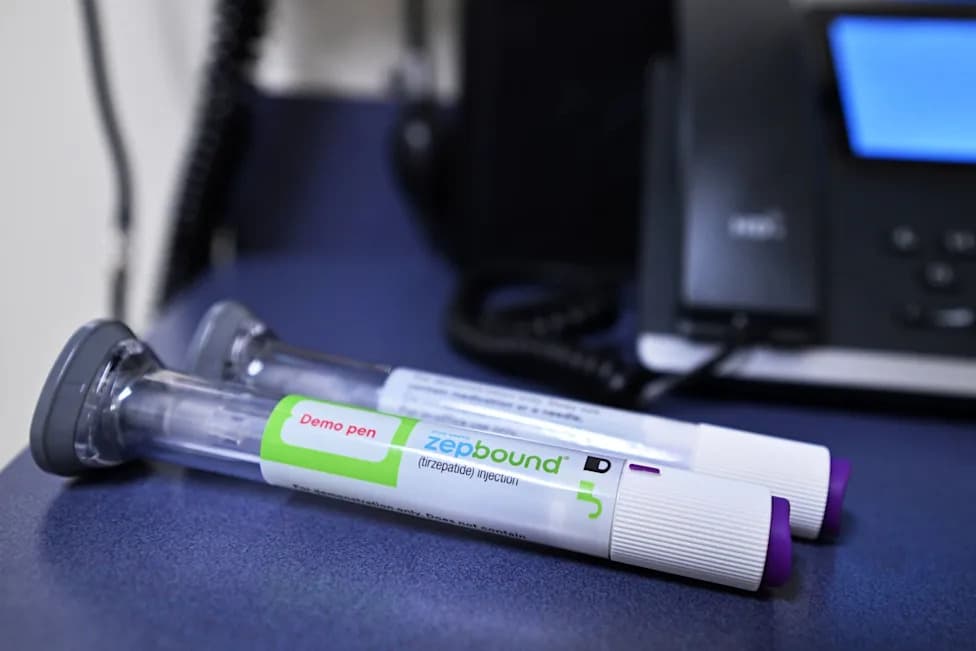
We are now on a familiar saviour‑to‑scare cycle with so‑called “fat jabs.” This week the Medicines and Healthcare products Regulatory Agency (MHRA) published figures associating weight‑loss drugs such as Wegovy and Mounjaro with 98 UK deaths, while some analyses suggest the total could be as high as 216. About 150,000 patients reported side effects, of which roughly 15,000–18,000 were classified as serious. The majority of reported fatalities have been linked to tirzepatide, the active ingredient in Mounjaro. Separately, an inquest heard that 73‑year‑old grandmother Caroline Savage died after increasing her Mounjaro dose and developing faecal peritonitis; other reports have cited intestinal disorders and pancreatic inflammation.
I should stress that millions now use these medications and most patients report important benefits — often dramatic weight loss and improved health markers. Many clinicians describe their effects as transformative. Yet caution is warranted. Quick fixes can produce unforeseen, costly consequences over time, and anecdotes from patients and clinicians raise legitimate questions about side effects and long‑term outcomes.
Anecdotal reports include loss of appetite that some users say drains pleasure from social life, alarming hair loss reported by some women (including public figures), and accounts of weight regained once treatment stops. Several people also describe a diminished “joie de vivre” while on the drugs. Conversely, others — including three friends of mine who accessed these treatments privately — have experienced greater wellbeing, reduced food cravings and renewed confidence in clothing and daily life.
Access and equity are additional concerns. A retired GP I met observed that the early beneficiaries tend to be relatively affluent people who can start and stop treatment at will, while many of the most disadvantaged, clinically complex patients face high thresholds for access and may only become eligible when their BMI and comorbidities are extreme. That raises uncomfortable questions about who benefits most from these innovations.
“It helped me lose a couple of stone,” my host told me after a brief trial, “but no one noticed, so what was the point?”
His rueful comment captures a wider truth: weight loss that is subtle may be personally satisfying but socially invisible, and for some the loss of appetite can erode simple pleasures such as sharing food and wine with friends.
The current data do not make the drugs villains in themselves — many people benefit and for some patients they may be life‑changing. But the MHRA’s figures, the clinical anecdotes, and equity concerns justify a measured, evidence‑focused response rather than blanket cheerleading. Policymakers, prescribers and patients should pursue a careful risk‑benefit assessment, monitor for rare but serious harms, and ensure fair access for those most likely to gain meaningful health improvements.
So forgive me if I don’t become an automatic cheerleader for Mounjaro and Wegovy. I relish food, drink and conviviality too much to want to silence them entirely — and I think that sensible caution, not hype, should guide how we use these medicines.
Miracle drugs? No. And now there is cause for careful scrutiny.
Help us improve.